GLP-1 Medication and Lipedema Surgery: Why My Approach Changed | Ditesheim Cosmetic Surgery
Lipedema / GLP-1 medication
GLP-1 Medication and Lipedema Surgery: Why My Approach Changed
Surgery takes the disease out. The medication takes the weight off.
Jeffrey A. Ditesheim, MD, FACS
Board certified, American Board of Plastic Surgery
Fellow, American College of Surgeons
Member, Lipedema Society — Surgical Standards Committee About Dr. Ditesheim →
Written and reviewed by Dr. Jeffrey A. Ditesheim ·
Reviewed September 2026 ·
Next review December 2026
My approach to lipedema has changed. For years it was immediate surgery. It is now a
combined approach: GLP-1 medication before surgery, surgery to remove the lipedema, and GLP-1
medication again afterward. This page explains why, describes the protocol I now use, and shows
my own patients photographed at each step — before surgery, after surgery, and after the
medication. I want to be clear at the outset that there are no published studies yet on GLP-1
medication in lipedema. What follows is what I have learned, offered because it has been
life-changing for so many of the women I treat.
Why my approach changed
Three things about this disease made surgery alone the wrong answer for many women.
1. Lipedema is an inflammatory disease
Lipedema fat cells do not work properly. Fluid collects around them, and the tissue becomes a
continuing source of inflammation — the swelling, the pain, the heavy legs. Controlling the
inflammatory triggers and their consequences is critical, and before the GLP-1 medications the only
anti-inflammatory strategy available was diet modification. These medications appear to have an
anti-inflammatory benefit of their own. Very frequently, women taking them describe less functional
disability — before anyone has operated on anything.
2. Obesity very often coexists with lipedema
Many of my patients describe large, uncontrolled weight gain, particularly at times of hormonal
flux — puberty, pregnancy, menopause. That extra weight changes the surgery. Removing
fifteen to twenty pounds of fat in one procedure is more dangerous and carries more complications
than a smaller operation. And a patient over 200 pounds carries greater intrinsic health risks
going into any surgery, which means a greater risk of surgical complications coming out of it.
3. Surgery is for the lipedema. Medication is for the obesity.
Surgery is the most critical part of treatment because it is the only thing that removes
lipedema tissue. But the ordinary obesity fat sitting alongside the disease does not need to be
removed surgically. It can be reduced medically with GLP-1 medication. Separating those two jobs
is the whole idea.
It may be that patients in Germany, where much of the surgical approach was developed, tend to
present at lower weights. When I visited the LipoClinic in Mülheim in 2024, the protocol was
still surgery — usually four consecutive procedures — and GLP-1 medication was not
being used at all.
What I saw in my own patients
More than anything I read, this is what changed my mind.
Large-volume fat removal can be very dangerous. Taking fifteen to twenty pounds of fat
in a single procedure has led, in my experience, to hospitalizations and blood transfusions. That
is not an acceptable routine risk for an elective operation.
Uncontrolled inflammation comes back. When the inflammation is not addressed, I have
watched it show up as early weight regain and as regrowth of lipedema — usually in another
part of the body, not the area that was treated.
Higher-weight patients need too many operations. For a woman at 200 to 300 pounds, the
amount of fat that would need to come out surgically requires multiple high-risk procedures. Some
women also lose substantial weight after surgery and are left with loose skin that a
different order could have avoided.
Enter the GLP-1 medications
When these medications arrived, the first thing I noticed was that weight loss on them was very
predictable. In my lipedema patients, tirzepatide — which acts on both the GLP-1 and GIP
pathways — seemed to work even better than semaglutide.
It is true that the adoption of GLP-1 medication in lipedema has come before the studies. To
date there are no published studies specifically looking at its benefit for lipedema patients. What
I can tell you is that, anecdotally and consistently, women describe both weight reduction and a
decrease in their inflammatory complaints: better mobility, less swelling, less pain. That
consistency, across many patients, is the basis for the combined approach I now use.
My treatment protocol now
1. Treat obesity first. GLP-1 medication to bring total body weight down before any
operation — especially weight above 200 pounds.
2. Treat inflammation for three months before surgery. GLP-1 medication continues, and
at the same time we address every other inflammatory trigger we can find. Some are intrinsic
— inflammatory conditions such as endometriosis or arthritis. Some are extrinsic, and diet
is the main one.
3. Treat the lipedema surgically, in fewer sessions. With the ordinary fat and the fluid
already reduced, what remains is the disease, and it can be removed more precisely and more
safely. After surgery, GLP-1 medication is resumed to control weight and, in my experience, to
help control progression of the disease.
A few caveats, stated plainly. This is my approach, and it is based on what is known about the
disease and on what I have learned from my own patients. Other lipedema surgeons may treat
differently. There are no published studies yet evaluating GLP-1 medication with lipedema, so this
is an off-label use at this time. I am not your prescriber, and this page is not a recommendation
of any particular product.
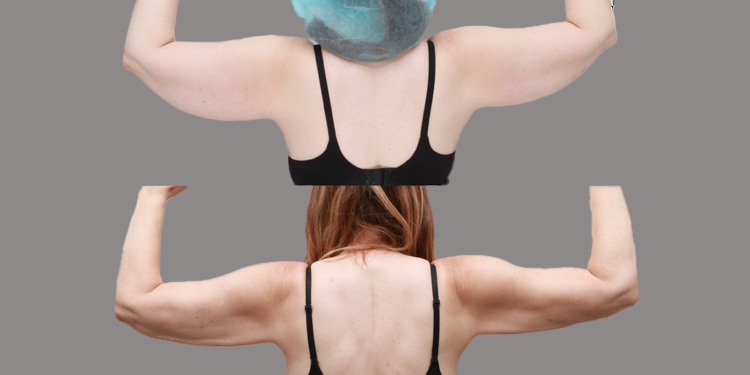
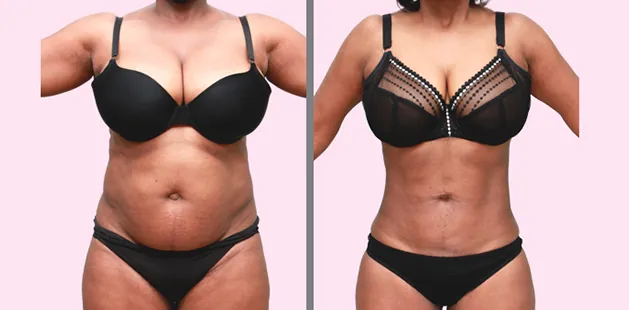
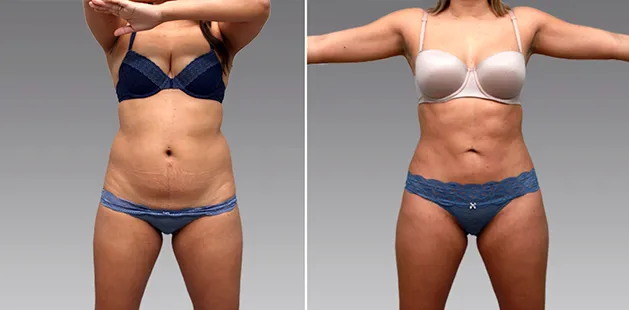
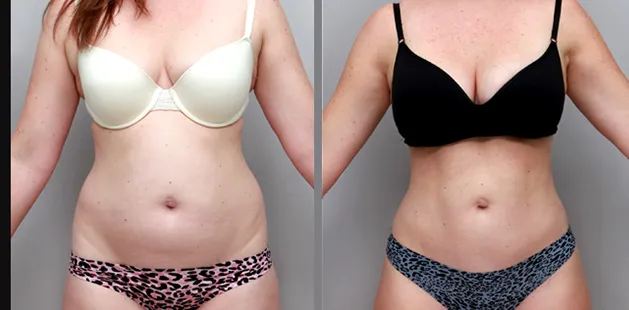
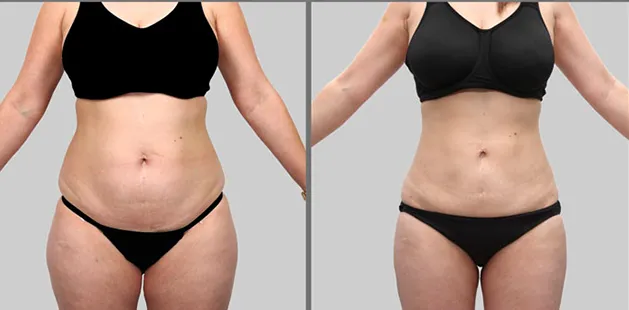
Size and shape: what the photographs show
This page exists to take one idea a step further than the
main lipedema page: to show
the same woman before surgery, after surgery, and then after GLP-1 medication at a lower weight, so
you can see for yourself what each one does.
The medication reduces weight by shrinking normal fat cells. Surgery removes the lipedema and
changes the shape of the limb. My patients put it better than I can: “With the GLP-1 my
size decreased. With surgery my shape changed.”
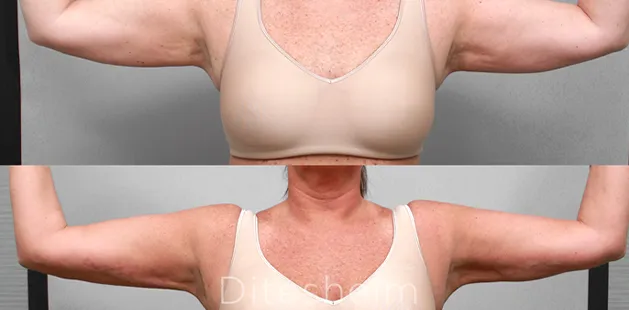
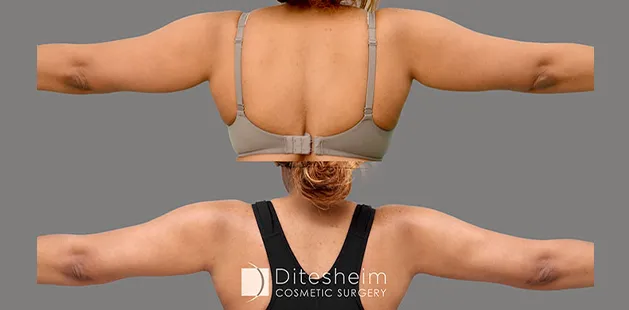
The other thing the photographs show is what does not change. Lipedema tissue is
different from normal fat and does not respond to GLP-1 medication. An untreated area with lipedema
keeps its shape no matter how much weight comes off. That is why surgery remains the mainstay of
treatment for removing the disease — and why, for a woman at 200 to 300 pounds, medication
first means a less risky operation, or fewer of them. Several of my patients have also stayed on the
medication after surgery as maintenance, to hold their weight and their result.
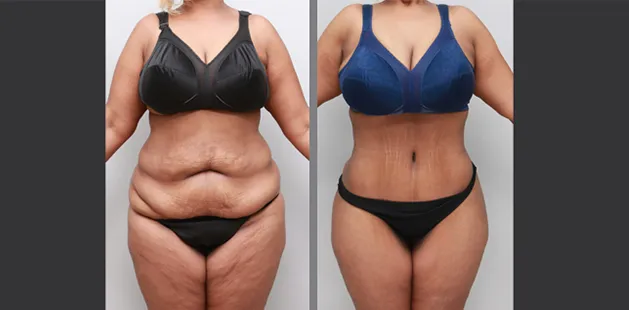
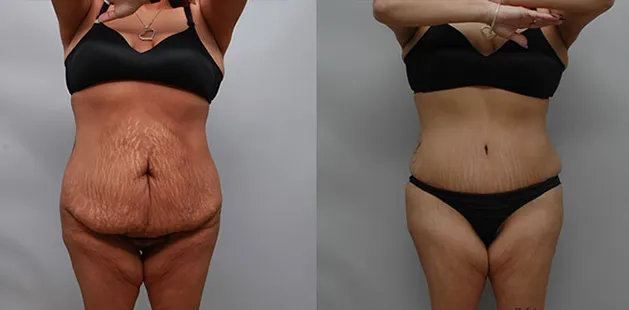
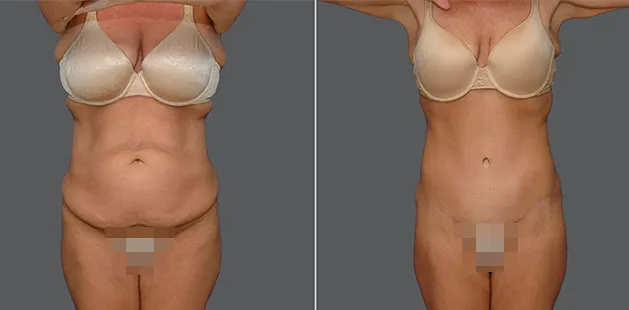
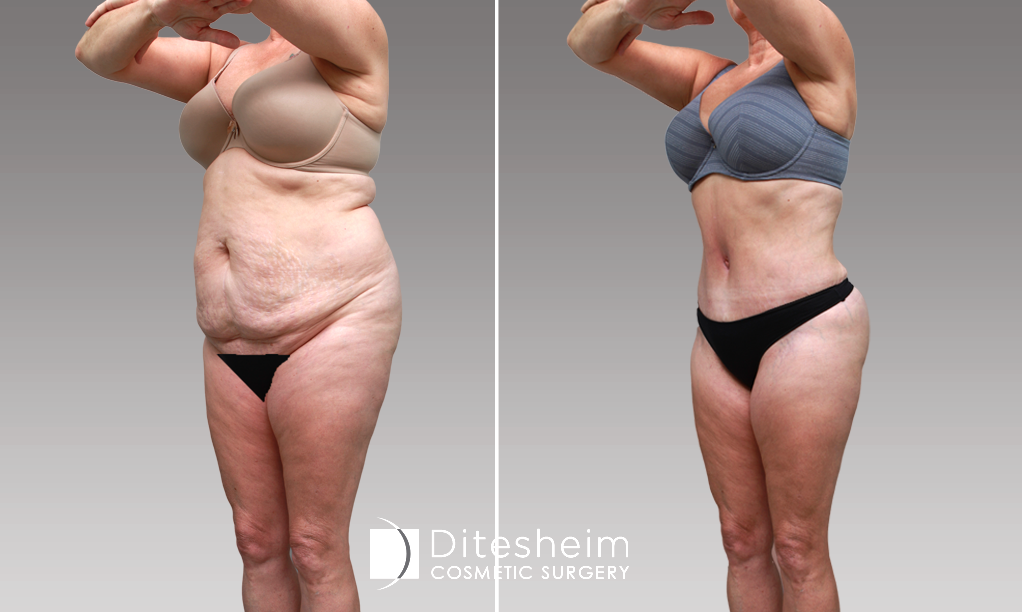
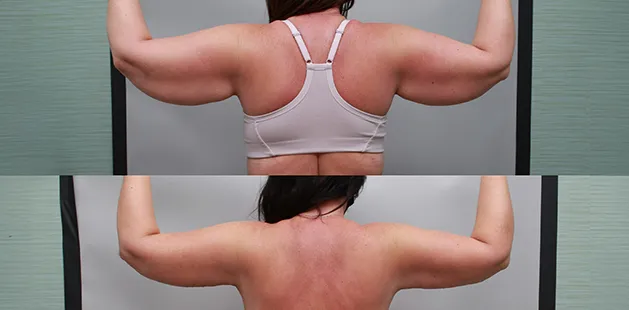
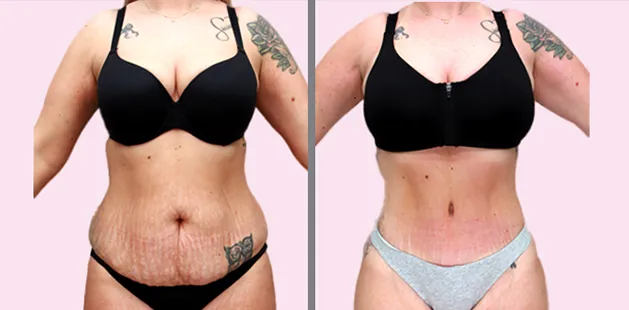
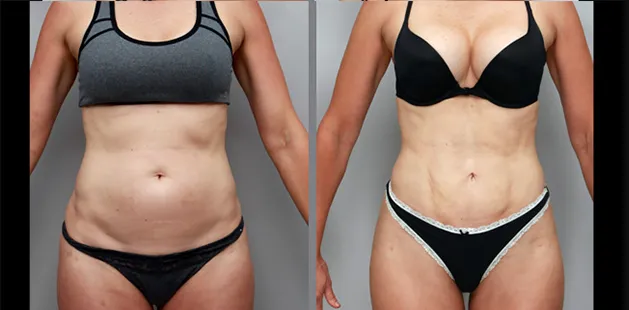
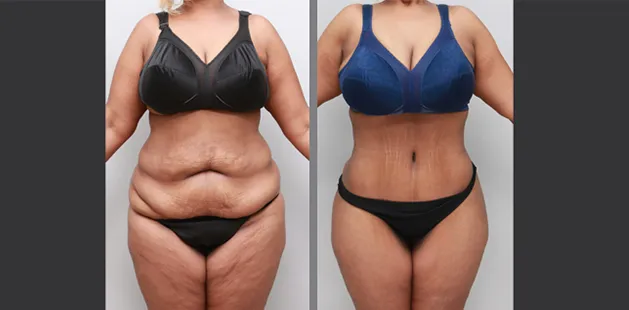
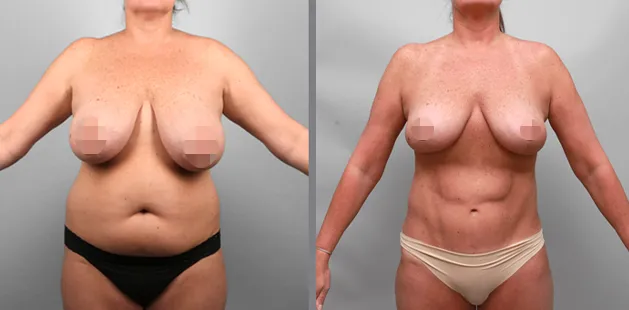
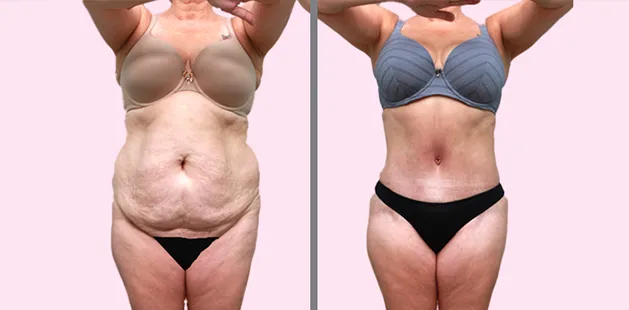
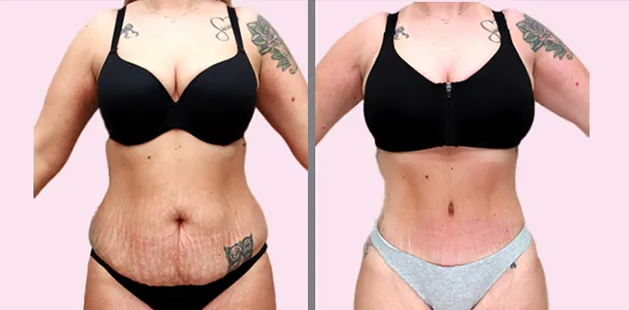
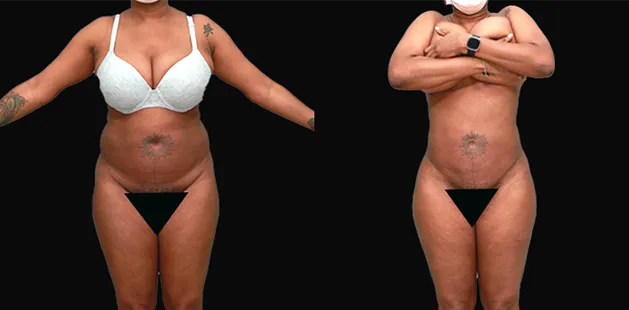
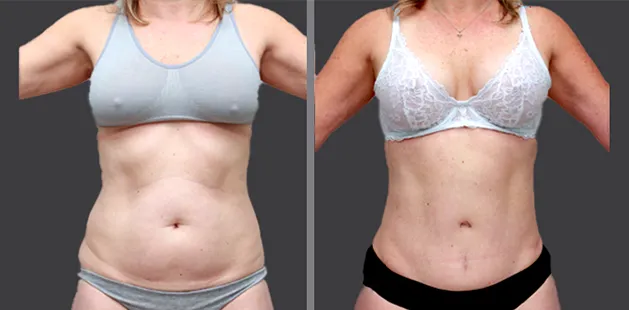
All photographs are of my own patients, published with consent and shown without retouching.
Read each case left to right.
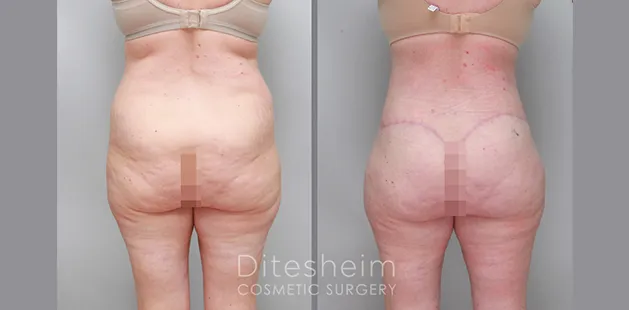
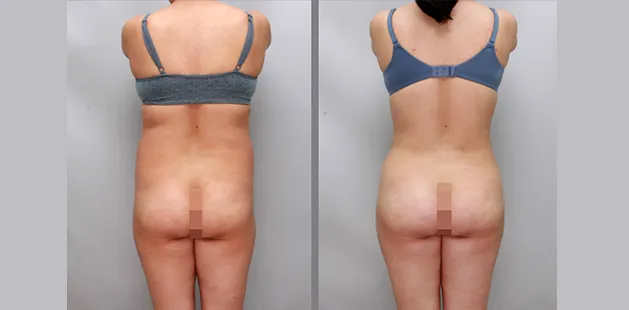
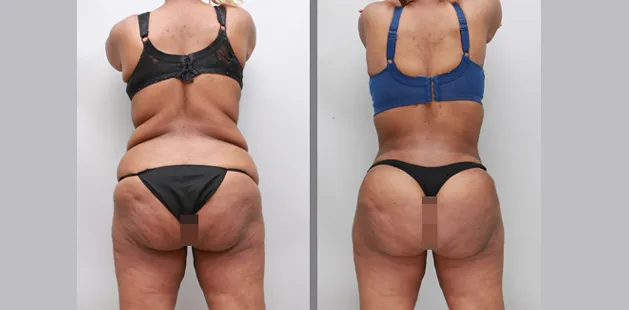
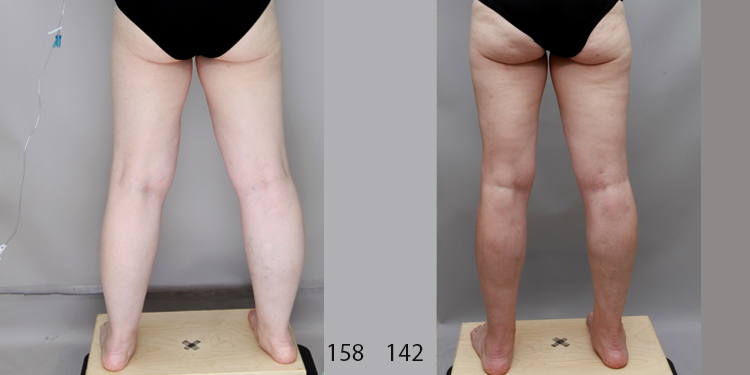
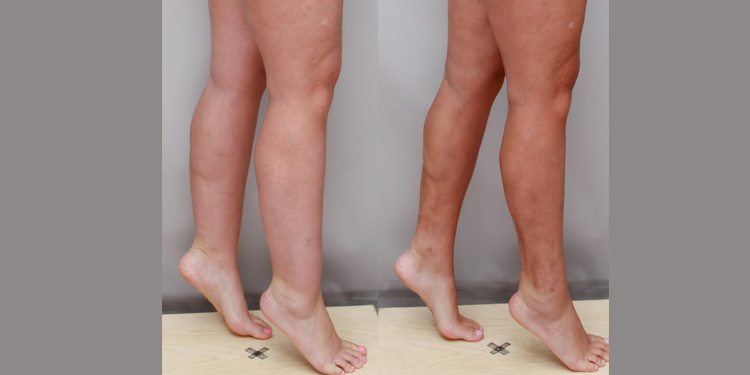
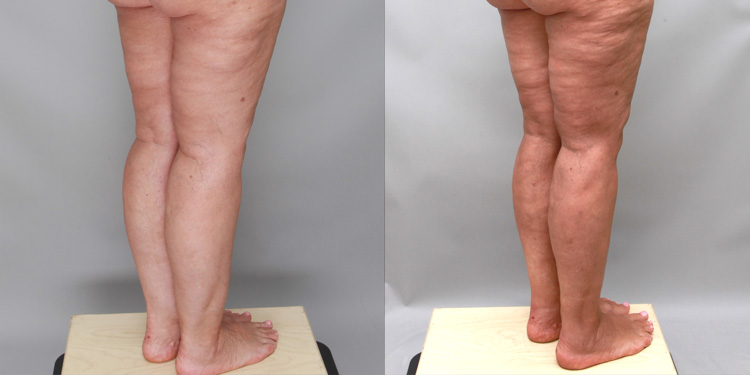
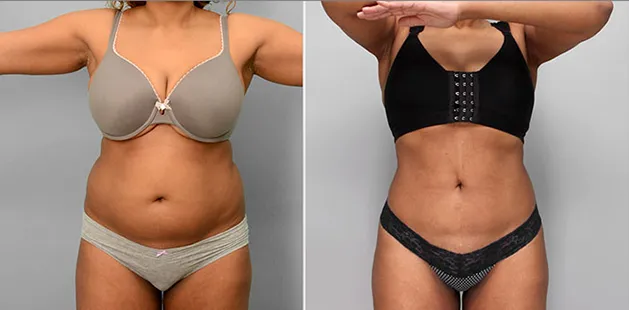
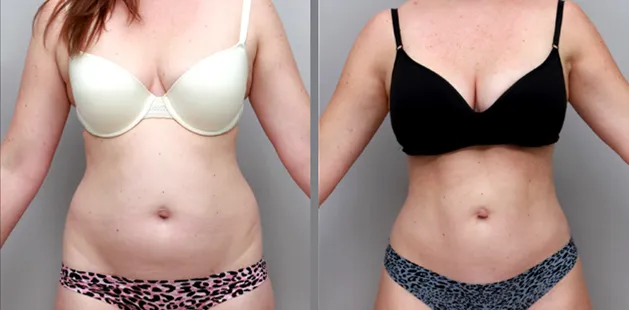
Case 01 · surgery, then GLP-1
Age 34 — the legs that did not change when the rest of her did
Before
142 lb · early-stage lipedema, lower body
After surgery
132 lb · buttocks, thighs and knees · shape corrected
After GLP-1
116 lb · one year later, no further surgery
Age
34
Treated surgically
Buttocks, thighs, knees · one session
Sequence
Surgery, then GLP-1
Weight on medication
142 to 116 lb
Time on combined treatment
One year
Change she reports
Significant relief of pain and swelling
The middle frame is what surgery does to shape, at essentially the same weight. The last frame
is twenty-six pounds off the medication — and the thing to look at is how little her lower
legs move between those two frames.
That is this page in one photograph. The weight came off everywhere the medication could reach.
It did not reach the lipedema still in her lower legs, and it never will. She is now on a
maintenance dose and we are planning her lower legs as the next area to treat.
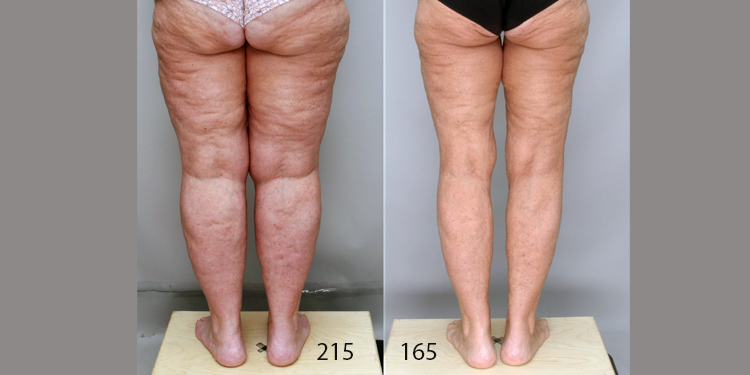
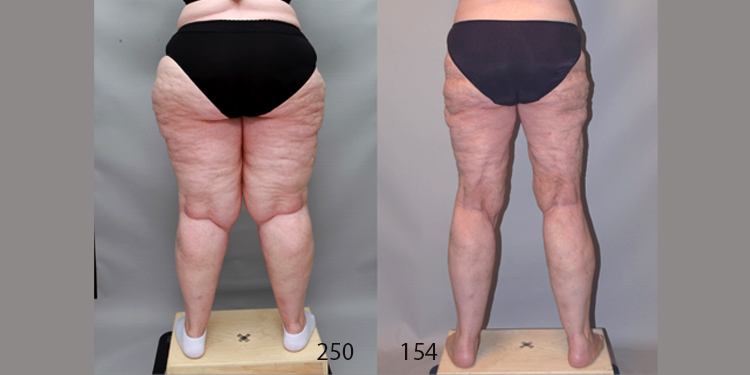
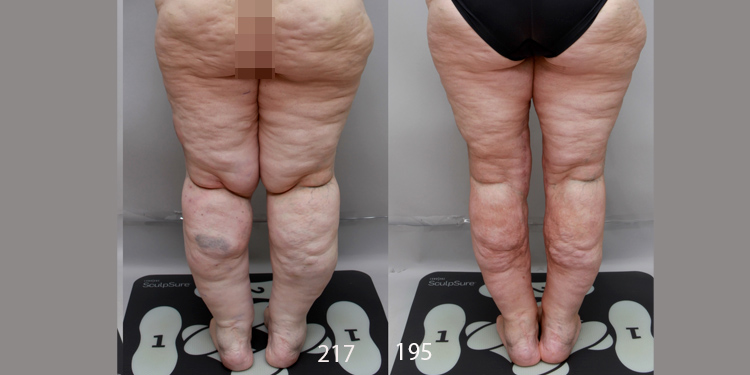
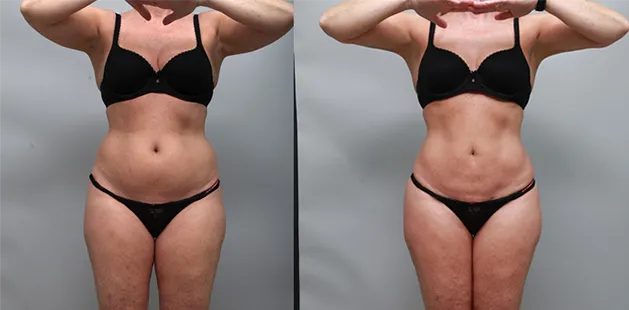
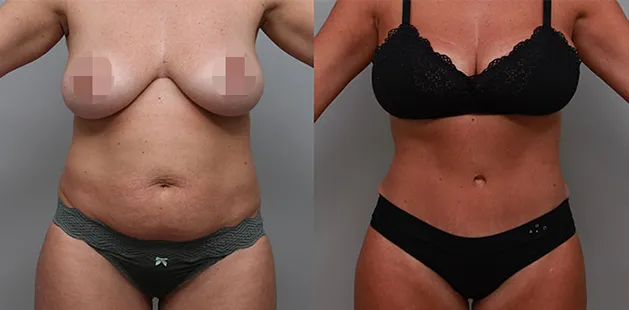
Case 02 · two surgeries at high weight, then GLP-1
Age 57 — one hundred sixty pounds off, and the order I would now reverse
Before
248 lb · extensive lipedema, lower body (high weight 300 lb)
After surgery #1
226 lb · 17 lb of lipedema fat removed
After surgery #2 and GLP-1
157 lb · six months later; she went on to reach 140 lb
Age
57
Treated surgically
Thighs, buttocks, saddlebags, knees · two sessions, four months apart
Sequence
Two surgeries at high weight, then GLP-1
Weight on medication
248 to 140 lb (160 lb total from a high of 300 lb)
Where she stands
Lipedema remains in untreated areas; further surgery planned at lower weight
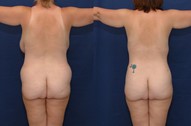
She had two surgeries. The first treated the anterior thighs and the saddlebags (lateral
thighs); the second, four months later, treated the posterior thighs, knees and buttocks. This
follows the German protocol for higher-weight women. In total, 39.5 pounds of lipedema fat were
removed in two sessions. The first frame is her at 248 pounds — her high weight was 300.
The middle frame is 226 pounds, after the first surgery alone removed 17 pounds of lipedema fat.
Between the middle and third frames she had her second surgery and started GLP-1 medication; the
third frame is six months later, at 157 pounds. She would go on to lose 160 pounds in all, from 300
to 140.
So many women present at very high weight. Lipedema treatment under the German protocol
meant removing large volumes of fat in four surgical sessions. This woman lost a very large
amount of weight with the benefit of two surgeries and GLP-1 medication. She is significantly
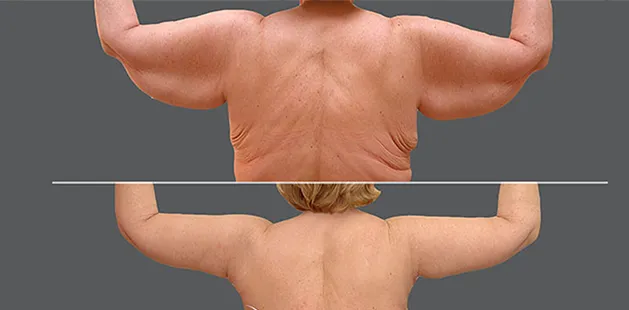
better functionally, and you can see her changed body shape. She will have significant skin
excess as a consequence. Today, treating her obesity first with GLP-1 medication and then
addressing her lipedema surgically may have been a safer and more efficient plan, with less risk
and less recovery.
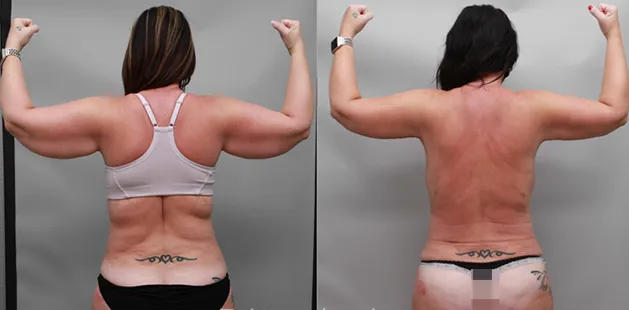
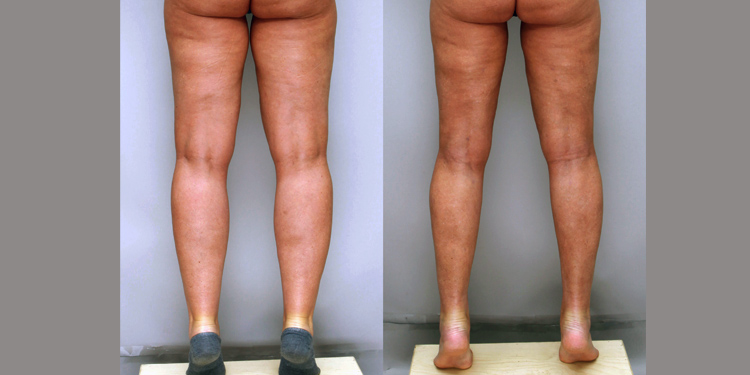
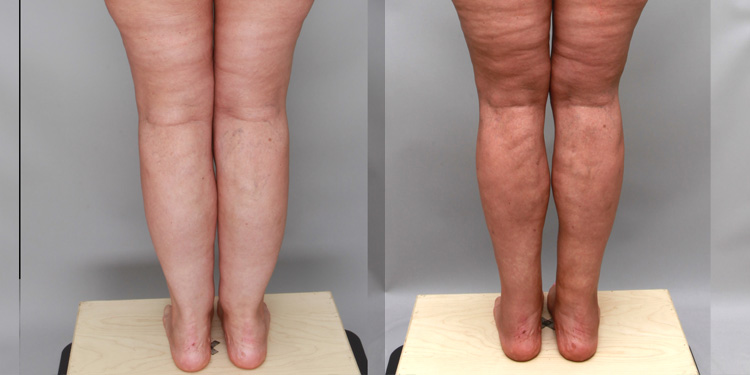
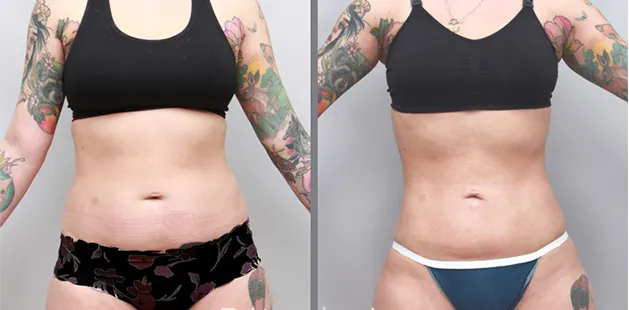
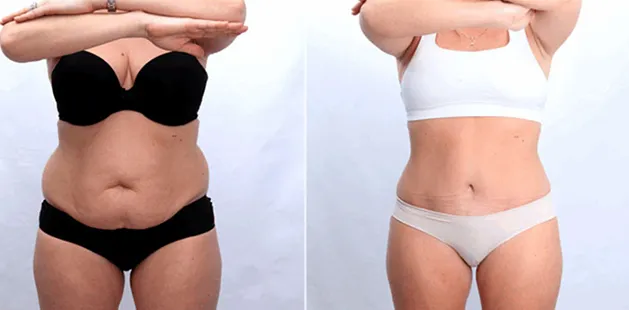
Case 03 · three surgeries, GLP-1 started after the second
Age 44 — three operations that might have been two
Before
180 lb · progressing lipedema, lower extremities
After surgery and GLP-1
137 lb · three sessions
Sequence
Medication started after the second operation
Age
44
Treated surgically
Buttocks, thighs, knees, legs · three staged sessions
Removed
37 lb of tissue
Sequence
Surgery, surgery, then GLP-1
Time on combined treatment
Nine months at 137 lb [update if a later follow-up is available]
Change she reports
Improved function and shape; still managing untreated areas
She presented at 180 pounds with significant pain, swelling and limited mobility, and a large
volume of disease. Thirty-seven pounds of tissue cannot come out in one setting under any
circumstances, so it was staged.
What I would do differently today. She began the medication after her second operation.
Had she started it before the first, the ordinary fat would have come down first, the remaining
disease would have been clearly demarcated, and I believe this would have been two operations
rather than three. Her case is a fair record of how my own thinking has changed, and I would
rather show you that than pretend the sequence was always obvious.
Individual results vary. All photographs are of Dr.
Ditesheim’s own patients, published with consent and shown without retouching.
DEV NOTE — Build as FooGallery PRO instances, not static images, so these
stay filterable with the rest of the lipedema gallery. Before/after labels stay as HTML text, never
burned into the JPEG — they must be indexable and screen-reader accessible. Serve WebP with
JPEG fallback; lazy-load everything below the fold.
What is not known yet
This area generates a lot of questions, and I want to be honest about which ones I cannot
answer.
Which medication is best for lipedema — tirzepatide or semaglutide?
Not known. Tirzepatide has seemed to work better in my patients, but nothing has compared
them in this disease. I am deliberately not presenting weight-loss literature here, because it
does not answer the lipedema question.
Does microdosing work?
Not known. There are no studies. I would rather say that than present information that does
not yet exist.
Can lipedema be controlled for more than two years with combined treatment?
This is the question that matters most, and the one I am watching in my own patients.
Surgery alone gave most women relief for up to about two years before the fat regrew and the
symptoms returned. Whether a combined anti-inflammatory and surgical strategy holds a result
beyond that is what we want to see.
Questions patients ask me about these medications
Broader questions about the surgery itself, staging and recovery are answered on
the main lipedema page.
Will GLP-1 medication shrink the lipedema in my legs?
No. Lipedema tissue is different from normal fat and does not respond to GLP-1 medication. The
medication shrinks normal fat cells, which reduces your overall size. Surgery is what changes your
shape, because surgery is what removes the lipedema. My patients describe it as: with the GLP-1 my
size decreased; with surgery my shape changed.
Should I take the medication before surgery or after?
In my practice, both. Before surgery, to bring total body weight down — especially above
200 pounds — and to control inflammation for about three months so the operation is safer
and needs fewer sessions. After surgery, to maintain weight and, in my experience, to help control
progression of the disease.
Is GLP-1 medication an approved treatment for lipedema?
No. There are no published studies yet evaluating GLP-1 medication in lipedema, and its use in
lipedema is off-label. What I describe here is my own approach, based on what is known about the
disease and what I have observed in my own patients. Other lipedema surgeons may treat
differently.
Which is better, tirzepatide or semaglutide? Does microdosing work?
The answer to both is not known. In my patients tirzepatide has seemed to work better, but that
is an impression, not a study, and no research has compared the two in lipedema or evaluated
microdosing. Those are decisions to make with your prescribing physician.
If your legs did not change when the rest of you did, that is worth an examination. A
consultation gives you a diagnosis, a stage, and a plan you can act on — including whether
medication before surgery is the right first step for you.