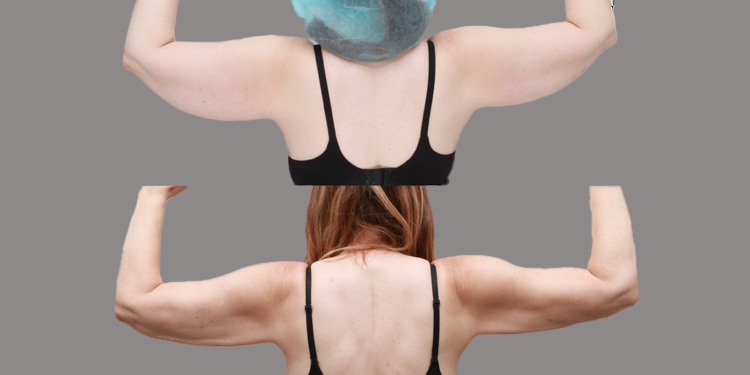
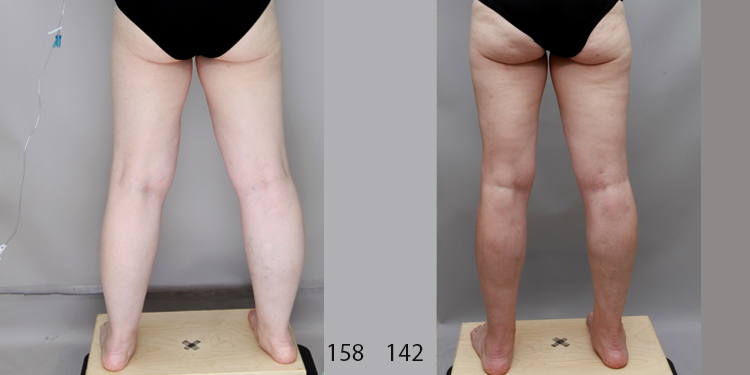
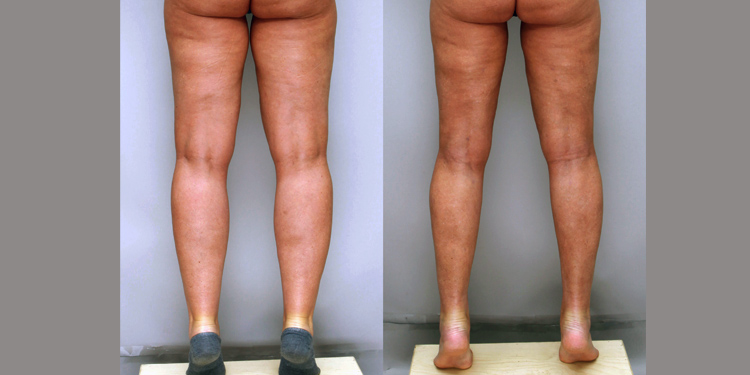
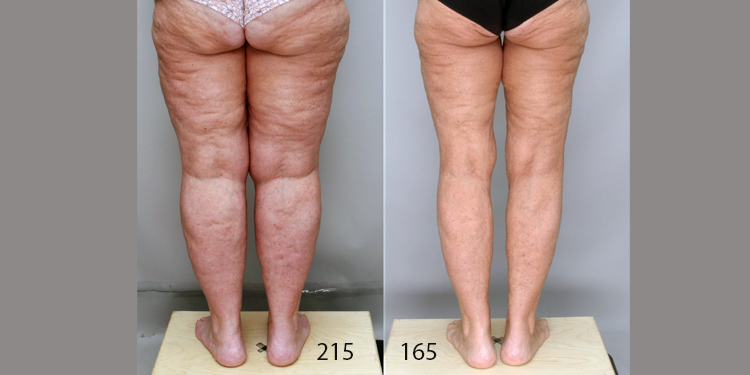
Ten questions, answered from the published evidence
Jeffrey A. Ditesheim, MD, FACS
Board certified, American Board of Plastic Surgery Fellow, American College of Surgeons Member, Lipedema Society — Surgical Standards Committee About Dr. Ditesheim →
Written and reviewed by Dr. Jeffrey A. Ditesheim
Reviewed August 2026 Next review November 2026
A disclosure. I perform this surgery, so I have a stake in the answers. Where the evidence is weak I say so, and every question below is rated for how solid the published evidence behind it actually is.
Short answers to what women actually ask me, each rated for how solid the published evidence behind it is. Open any question for the detail and the studies it rests on.
Ten questions, answered from the published evidence
01 ·
Strong evidence
Will surgery reduce my pain?
Yes — this is the most reliable benefit of the operation. In the randomized trial 68% had significantly less leg pain at twelve months, against 7.6% on conservative therapy. In survey data, of women who had pain beforehand, 86% reported it reduced.
Detail and sources
Pain responds most consistently and most quickly of any symptom. Lipedema tissue is a continuing source of inflammation and the pain is largely pressure-related — remove the tissue and you remove the source. Wollina measured it directly in 111 women with advanced disease: median pain 7.8 before treatment, 2.2 after.
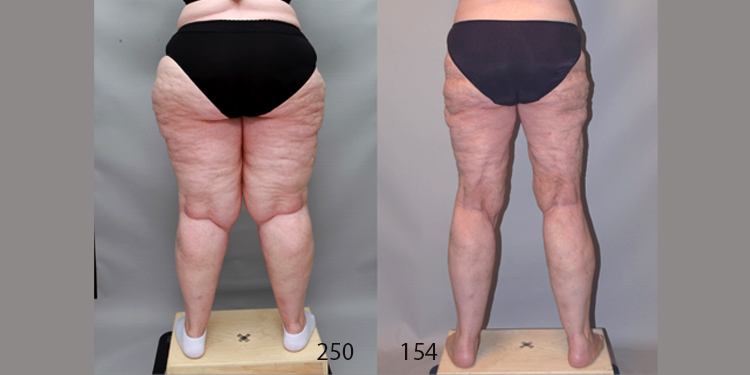
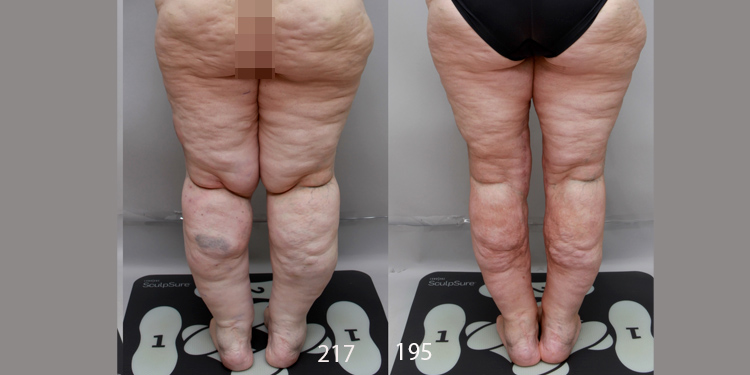
What I see in practice. Most women tell me the lipedema pain is gone before the surgical soreness is. They can usually tell the two apart. I prioritize the areas that hurt most when planning which regions to treat first.
Sources
LIPLEG — Podda et al., protocol 2021; 12-month results reported via the G-BA, 2025. RCT, n=410. Pain reduction 68.3% vs 7.6%, OR 26.3. doi:10.1186/s13063-021-05727-2 · NCT04272827
Will the swelling improve, and can I stop wearing compression?
Swelling improves for most women, and a substantial minority come off compression entirely. Of those with swelling beforehand, 36% said it resolved; 30% stopped compression garments within three months. In early-stage disease the effect is larger — in one stage 1–2 group, the need for any conservative treatment fell from 100% to 44%.
Detail and sources
I want to be careful not to oversell this. Swelling is more variable than pain and depends on how long you have had the disease and how much of the area is treated. Women with longstanding or advanced lipedema often still need some compression, though usually less and lighter. Bruising follows a similar pattern — 90% before surgery, 43% after.
What I see in practice. Compression before surgery matters more than most people expect. I require at least three weeks of flat-knit compression and decompressive treatment beforehand, because reducing limb fluid first measurably improves recovery.
Sources
Witte 2020 — prospective, stage 1–2, n=63. Need for any conservative treatment 100% → 44%; manual lymphatic massage 89% → 40%. doi:10.1016/j.bjps.2020.03.002
Dadras 2017 — reduced need for decongestive therapy, greater in stage 2 than stage 3. Arch Plast Surg 2017;44(4):324–331
03 ·
Strong evidence
Will I move and walk better?
Yes, and it is measured objectively rather than only self-reported. 70% of surgical patients in the trial showed major functional improvement, against 10% on conservative care. Wright measured actual knee mechanics and found gains comparable to published results for total knee replacement.
Detail and sources
This is the finding that surprises physicians most, so it is the one worth showing your doctor. Wright did not only ask women how they felt — knee range of motion, gait and joint kinematics were measured clinically and compared against the knee replacement literature.
The mechanism is straightforward. Lipedema of the thigh and knee loads the knee and ankle continuously, which is why stairs become difficult. Remove the mass and the mechanics change. In survey data 81% said lipedema interfered with walking; afterward walking improved in 96% of stage 3 and 88% of stage 2 patients, and 82% were back to normal activity within a month.
Sources
Wright 2023 — n=189 patients, 507 procedures; PROMIS, RAND SF-36, knee kinematics and bioimpedance analyzed in 66 of the 189, follow-up to 4 years. doi:10.1097/GOX.0000000000005436
LIPLEG — protocol 2021; 12-month results via the G-BA, 2025. Physical function 70% vs 10%, OR 21.0. doi:10.1186/s13063-021-05727-2
Should I have surgery now, or wait until it gets worse?
Earlier is better, and the evidence is not ambiguous. Every study comparing stages found women treated earlier did better — more complete relief, less ongoing need for compression and lymphatic therapy, less residual disease. The randomized trial settled the remaining question: benefit was significant at every stage, including stage I. Nothing supports waiting until you are more disabled.
Detail and sources
The pressure usually runs the other way — you will be told to try conservative treatment longer, lose weight first, come back when it is worse. Waiting is not neutral. Lipedema is progressive, and tissue left in place keeps producing inflammation.
In early-stage groups the need for manual lymphatic drainage fell from 89% to 40% after surgery, and the need for any conservative treatment at all from 100% to 44%. Dadras concluded directly that because secondary lymphedema develops in later stages, liposuction should be standard therapy early.
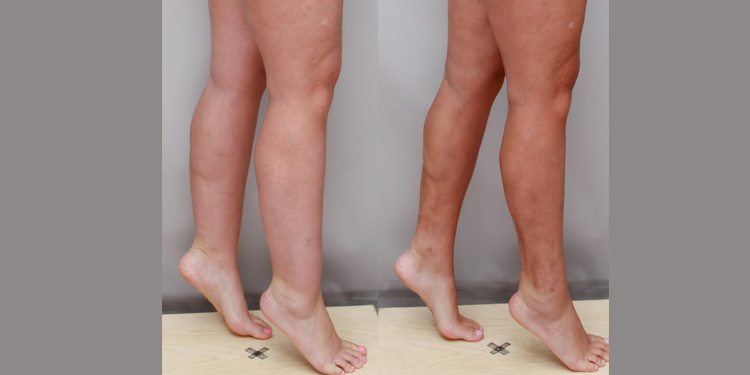
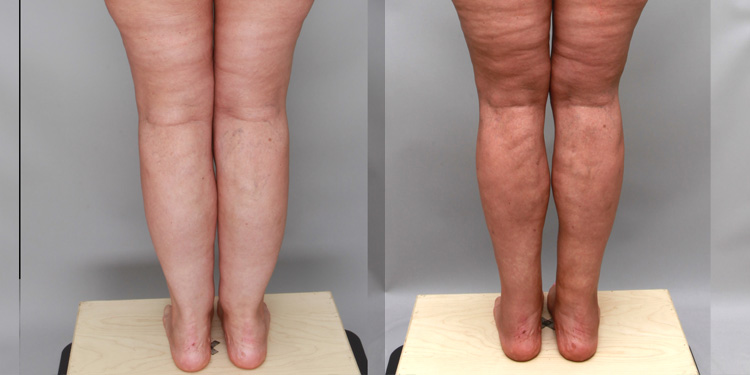
What I see in practice. One patient came to me at 59 with advanced disease. Four years on she is significantly better and would tell you it was worth it — but she still has lipedema pain and swelling, and always will. Compare a woman I treated at 30 with early disease and one operation: at sixteen months, no pain, full mobility, off medication. Both are good outcomes. They are not the same outcome, and the difference is when they came through the door.
The honest caveat: nobody has randomized women to operate now versus in five years, and nobody will. The early-is-better conclusion comes from comparing stages across cohorts — strong, but not a direct test.
Sources
LIPLEG — protocol 2021; 12-month results via the G-BA, 2025. Effects consistent across stages I–III; cited by the G-BA in extending coverage to all stages. doi:10.1186/s13063-021-05727-2
Dadras 2017 — benefit greater in stage 2 than stage 3; recommends early-stage surgery to prevent secondary lymphedema. Arch Plast Surg 2017;44(4):324–331
In treated areas the improvement appears to last. Baumgartner followed 60 women for twelve years and found gains in pain, sensitivity, swelling, bruising and movement persisted without meaningful worsening. But untreated areas keep progressing — and that is where most of the confusion comes from.
Detail and sources
Surgeons tend to say lipedema does not return if the fat is fully removed. Women frequently report that it feels like it does. The truth usually sits with the patients, and the explanation is one of two things: disease progressing in areas never treated, or weight gain adding normal fat over a treated limb.
Note what the twelve-year study is and is not — one study, 60 women, a single treated cohort. Much the best durability data available, but not a randomized comparison.
What I see in practice. Weight gain, more than age, seems to drive progression. One patient had her arms and lower legs treated but left her thighs alone; at six months the legs looked excellent and the thighs were visibly larger. Nothing came back — the untreated area simply carried on.
Sources
Baumgartner 2021 — longitudinal at 4, 8 and 12 years, n=60. Phlebology 2021;36(2):152–159 · doi:10.1177/0268355520949775
Schlosshauer 2021 — disease-specific quality of life. Int Wound J 2021;18:923–931
06 ·
Moderate evidence
How many operations will I need?
Historically two to four. In current practice, often fewer. Published series average two to four sessions, with 10–12 lb removed per procedure and about 28 lb across a full course. The number is driven by a safety limit, not preference: outpatient surgery caps aspirate at roughly 10 lb per session.
Detail and sources
Note how far this sits from cosmetic liposuction. These are large-volume circumferential debulking procedures on diseased tissue.
The published averages come from an era when surgery was the only treatment. When normal body fat is reduced medically beforehand, the remaining lipedema tissue is easier to identify and remove precisely, and the volume ceiling covers more of the disease.
What I see in practice. Most of my patients have had one or two operations; only a few have needed three. This is ahead of the published literature rather than supported by it — no study has yet tested medical pre-treatment against standard sequencing.
Should I lose weight first? Does GLP-1 medication help?
Two questions with two different answers. Will losing weight fix your lipedema? No — lipedema tissue does not respond to caloric restriction, and bariatric surgery does not remove it either. Should you lose weight before surgery anyway? In my view yes, for most women — but that is my clinical judgement, not a finding from the literature.
Detail and sources
Reducing normal body fat before surgery does three things: it makes the operation safer, makes the diseased tissue easier to identify and remove precisely, and often reduces the number of procedures needed. It is preparation for surgery, not a substitute for it.
What I see in practice, and how my view has changed. One patient had three operations and only started GLP-1 medication after her second. Today I would encourage the medication first. A woman at 260 lb brought down to 170 lb leaves isolated fibrotic lipedema tissue that can be addressed in one or two procedures instead of three or four, and heals at the lower weight with less complication risk. I am direct that the published evidence has not caught up with this.
Sources
Herbst 2021 — conservative treatment reduces tissue fluid but not lipedema tissue; bariatric surgery not effective for lipedema. doi:10.1097/GOX.0000000000003553
US Standard of Care 2021 — graded consensus statements; predates the GLP-1 era entirely. doi:10.1177/02683555211015887
Done correctly, no — the opposite. Lipedema is not a primary disease of the lymphatics; the channels are obstructed by abnormal fat growth. Remove the obstruction and drainage can return toward normal. De Souza demonstrated this with lymphoscintigraphy before and after surgery.
Detail and sources
“Correctly” and “can” are doing real work in that answer. Poorly performed liposuction absolutely can injure lymphatics. That is why lipedema surgery uses a modified technique: treating in the axis of the limb rather than across it, working with awareness of where the major lymphatic vessels run, avoiding overdistention with fluid, and using gentle power-assisted or water-jet methods.
Damage to the blood supply just under the skin, trauma to lymph channels, or operating on later-stage disease can produce secondary lymphedema, sometimes six to twelve months later. This is the strongest argument for choosing a surgeon by lipedema experience rather than general credentials.
Sources
de Souza 2023 — case report with lymphoscintigraphy; drainage returned toward normal. One patient only. doi:10.1097/GOX.0000000000005097
The honest answer is that the published literature reports complications inconsistently, and that is a real gap. Where they were reported, they included secondary lymphedema with foot and ankle swelling, skin changes including fibrosis and pigment irregularity, phlebitis, post-surgical anemia, one pulmonary fat embolism and one thrombosis.
Detail and sources
I would rather show you this than leave it out. Every study on this page reports benefit; fewer report harm carefully, and a page quoting only the benefits would mislead you.
On mitigating risk: these are large-volume procedures and volume is where the danger sits. The outpatient limit exists for that reason, and Germany’s guideline caps aspirate at 8–10% of body weight per procedure. Operating on women at very high weight and removing very large volumes is the highest-risk combination — another reason I favor reducing normal body fat medically before operating. All my surgery is performed in our QUAD A accredited outpatient facility, the highest accreditation level for general anesthesia.
Sources
On the complication evidence itself. It is genuinely scattered and unpooled. No study or review has aggregated complication rates across the published series. The events listed above are drawn from individual reports that differ in how they defined, sought and counted adverse events. Read them as a description of what has been reported, not as a rate — and understand that the absence of a pooled figure is itself a limitation of this literature.
German S2k guideline 2024 and G-BA surgical guideline 2025 — aspirate capped at 8–10% of body weight per procedure. g-ba.de
10 ·
Moderate evidence
How do I know whether a surgeon is qualified to do this?
Board certification alone does not tell you. An excellent board-certified plastic surgeon may never have treated lipedema. Germany set a standard in 2025 — at least 50 independent lipedema operations, or 20 supervised within two years. There is no American equivalent, so you have to ask.
The questions to ask any surgeon
Ask these of anyone you consult, including me. A surgeon who does this work regularly will have ready answers.
How many lipedema operations have you performed? Not liposuctions. Ask for a number.
Do you use lymph-sparing technique, and how? Working in the axis of the limb, avoiding overdistention, gentle power-assisted or water-jet methods.
Do you map veins and lymphatics before operating? Doppler or ICG lymphography.
How much will you remove, and what is your limit? A surgeon without a stated limit is a concern.
Will you treat the area circumferentially? Partial treatment gives partial relief.
Who manages my lymphatic care afterward? A surgeon working alone on this is a warning sign.
What happens to areas you do not treat? Honest answer: untreated lipedema keeps progressing.
Sources
G-BA surgical guideline 2025 — 50 independent or 20 supervised operations; aspirate capped at 8–10% of body weight; diagnosis confirmed by two physicians. Set out in full, with the decision documents, in the G-BA surgical guideline, in full.
US Standard of Care 2021 — recommends surgery after failed conservative measures, but sets no surgeon case-volume requirement. doi:10.1177/02683555211015887
Who decides what good lipedema care is: the US standards are being written now
For most diseases a specialty society writes a standard, insurers build policy on it, and medical schools teach it. Lipedema has not had that. It has had scattered individual physicians, mostly self-taught, reading German literature and working it out patient by patient.
That is why your primary care doctor may never have heard of lipedema. There has been very little settled material to teach them.
The 2021 Standard of Care for Lipedema in the United States — the graded consensus statements cited throughout this page — is now five years old. It predates the randomized trial, predates Germany’s coverage decision, predates what we have learned about GLP-1 medication, and sets no requirement for how much lipedema experience a surgeon should have.
The lipedema physicians in this country have since organized into the Lipedema Society. I serve on its Surgical Standards Committee, and we are writing the US surgical standards now. I will not characterize what that document will say before it exists.
Why this matters to you. A standard is not only a document for surgeons. It is what your primary care doctor can look up, what a therapist trains against, and what gives you something to point at when you are told this is just obesity. Eventually it is also what makes credentialling checkable, so question 10 has an answer you can verify rather than a list you have to ask.
What the research still cannot tell you
How long the randomized benefit holds.
LIPLEG has reported at twelve months; 24-month data is expected in 2027.
Whether treating early actually prevents late disease.
The stage comparisons are consistent, but nobody has randomized women to operate now versus later.
How GLP-1 medication and surgery interact.
The biggest gap. My position on sequencing is clinical judgement, not established fact.Complication rates.Reported inconsistently across the series, and never pooled. Reviewers are right to raise this.Which women do best.No study has identified who responds most, by age, stage, distribution or family history.
If you want to talk about your own case. This page is the evidence. The lipedema page explains how I diagnose and treat it. The consultation is where the two meet your particular anatomy, stage and history.
Written and reviewed by Jeffrey A. Ditesheim, MD, FACS · Ditesheim Cosmetic Surgery, 9336 Blakeney Center Drive, Suite 130, Charlotte, NC 28277 · 704-542-8686. Reviewed August 2026, next review November 2026. This page summarizes published research and is not a substitute for individual medical advice.