
Lipedema Treatment in Charlotte, NC
you were told wrong.
Jeffrey A. Ditesheim, MD, FACS
Written by Jeffrey A. Ditesheim, MD, FACS · October 2026 – About Dr. Ditesheim →

Jeffrey A. Ditesheim, MD, FACS
Board certified, American Board of Plastic
Surgery · Member, Lipedema Society
- 30 Years – 5,000+ Surgeries
- Lipedema Society, Surgical Standards Committee
- National surgical guidelines panel
- Presented at FDRS
- QUAD A accredited facility
If you are trying to find out what is wrong
01
Do I have lipedema?
The four symptoms that separate it from fat
02
What else points to lipedema
Bruising, hypermobility, family history
03
What lipedema actually is
An inflammatory disease, not a weight problem
04
Four things you have been told that aren’t true
Obesity, lymphedema, surgery, recurrence
05
Where do I go to get diagnosed?
Why most doctors miss this
06
The questionnaire I use in my office
Free, and yours to bring to any doctor
If you already know you have it
07
Why surgery alone stopped being the answer
What changed, and why it matters
08
How is lipedema treated
The surgical half and the medical half
09
My patients’ results — six cases
Six women, ages 30 to 59, with the numbers
10
Recovery, honestly
Preparation, timelines, what it really involves
11
What happens at a consultation
Diagnosis, plan, and what you leave with
12
What I’ve done in lipedema specifically
Training, guidelines work, credentials
13
Questions women ask me
Nine of them, answered plainly
Do I have lipedema?
Start with shape, then with function. Almost every woman I diagnose recognizes herself in both halves of what follows — usually years before anyone gave it a name.
Where the fat sits. Most commonly it is disproportionate fat in the lower body and extremities: the pelvis — hips, saddlebags, outer thighs — and the thighs and knees. Many women, though not all, also have it in the legs below the knees, and in the arms and forearms.
Heavy legs
Women describe this the same way almost word for word. Not sore, not tired — heavy. A weight you are carrying rather than a body you are moving.
Pressure pain
The pain is usually pressure-related, like a child or an animal sitting on your lap. With thigh and knee involvement it loads the knee and ankle joints, and stairs become difficult. There can be hip, knee, ankle or foot pain.
End-of-day swelling
Worse after long standing or long sitting, better overnight — until it isn't. Over time the swelling can become constant and stop resolving.
Loss of mobility
Difficulty standing through a working day. Stairs, hikes and travel become things you plan around. This is the part that most often brings a woman to my office.

The knee fat pad. Marked here before surgery. These deposits on the inner knee are very common in lipedema and are one of the findings I look for on examination.

Below the knee. Where the calves are involved, the fullness stops abruptly at the ankle and the feet look normal. That shelf — the cuff sign — is one of the most reliable findings there is.
What else points to lipedema?
- Easy bruising — marks you can't account for.
- Joint hypermobility.
- Certain food intolerances.
- Family history — a mother, grandmother or sister with the same body or the same diagnosis.
- Large weight gain with fat growth outside your control, particularly when hormones are in flux: puberty, pregnancy, menopause.
One important exception: lipohypertrophy
Some women have disproportionate fat distribution in the lower body and extremities and no symptoms at all — no pain, no swelling. Anatomically it can look exactly like lipedema. It isn't.
This distinction matters, because lipohypertrophy may respond to medical treatment alone. If that's what you have, I would rather tell you that than operate on you. Part of what a proper examination is for is ruling this in or out.
What lipedema actually is
Like so many medical conditions, lipedema was first defined by what doctors observed — in Germany, in the 1940s. Women were presenting at higher weight with strange, exaggerated fat growth in the lower body and extremities, and someone finally wrote it down.
Over the eighty years since, through dedicated centers and publications, most of them German, it has come to be understood as an inflammatory disorder of fat cells (the studies behind that). The cells don’t work properly. Fluid collects outside them. That is what produces the swelling and the pain.
There is a known genetic and hormonal component, and you can see both in the pattern of who gets it: the strong family history, and the way the disease progresses at exactly the moments when hormones are in flux — menarche, pregnancy, menopause. Why that argues for treating earlier →
That eighty-year body of work is also where my own technique comes from, which is why I went to Germany to see it practiced.
Four things you have probably been told that aren't true
“Lipedema is the same as obesity.”
“Lipedema and lymphedema are the same.”
Lymphedema is a failure of the lymph channels, and it swells the whole limb, hands and feet included. In lipedema the channels work but are blocked by diseased tissue, so the feet stay normal, and removing that tissue can restore normal lymph flow. Late in the disease the two can occur together.
“Surgery is the only treatment for lipedema.”
This was true until about a decade ago. It isn’t now; treatment is medical and surgical together, and section 07 explains why.
“It will come back no matter what I do.”
Lipedema is progressive, which means that without intervention it does get worse with time. That part is true, and it is why waiting is not a neutral choice. With combined treatment the disease can be controlled without progressing to disability.
Where do I go to get diagnosed?
There are primary care doctors, vascular specialists and plastic surgeons with a dedicated interest in lipedema. They are worth finding.
A great many good doctors — primary care physicians, orthopedists, obesity specialists — are simply not familiar with lipedema. It isn’t indifference. It’s that awareness of this disease has not reached most of practicing medicine. And if your doctor doesn’t know what lipedema is, you cannot be diagnosed with it. What happens instead is that you are told it’s obesity, and to lose weight through diet and exercise.
You then spend years doing exactly that, watching it not work, and being told to try harder. I have listened to a version of that story from nearly every woman who has sat in my office. The despair that comes out of it is real, and it is why so many women end up finding their answers from each other on social media rather than from a physician.
There are primary care doctors, vascular specialists and plastic surgeons with a dedicated interest in lipedema. They are worth finding. The questionnaire below is a starting place — take it with you.
“If your doctor doesn’t know what lipedema is, you can’t be diagnosed with it. That isn’t your failure.”
Dr. Jeffrey Ditesheim
The questionnaire I use in my own office.
I built this to score what actually matters in lipedema — mobility, pain, swelling, shape — and to track whether treatment is working. I’m making it public because the hardest part of this disease is getting anyone to take it seriously, and walking into an appointment with your symptoms already written down changes that conversation.
Two tools, two jobs
Nine quick questions on shape and symptoms. Tells you whether what you’re experiencing looks like lipedema and is worth pursuing.
- Takes two minutes
- Answered on this page
- Nothing to fill in or send
The full form. Scores mobility, pain, swelling and shape from 0 to 10, and records weight history, family history, hormonal triggers, diet and what conservative treatment you’ve already tried.
- Print it and take it to your doctor
- Gives you a baseline to measure against
- Bring it to a consultation with me
If the doctor you take it to is unfamiliar with lipedema, take the evidence as well: the eight studies worth citing, and what each one proves — written to be printed and handed across a desk.
Start here · nine questions
Does this sound like your body?
Tick everything that is true. Nothing is sent anywhere, nothing is stored, and there is no email box at the end of it. These are the nine things I listen for when a woman describes her legs to me for the first time.
This is not a diagnosis, and it is not meant to replace one. It is a way of organizing what you already know about your own body so that someone qualified can look at it properly.
If you already know you have it
Everything above is written for the woman who is still trying to find out what is wrong with her. What follows is for the woman who already knows, and is deciding what to do about it — how this disease is treated now, what my patients actually look like, and what the process involves.
Why surgery alone stopped being the answer
Surgery alone became a short term solution. Current treatment often involves the use of GLP-1’a and surgery for long term benefits.
I am a surgeon telling you that the surgical standard I was trained into did not hold. It matters that you hear this from me rather than discover it two years after an operation.
Until the last decade, lipedema was considered a surgical disease. Women were referred to specialized centers where successive procedures removed the diseased fat. Those procedures worked — they gave immediate relief, because lipedema fat is itself a significant and continuing source of inflammation. Take it out and the symptoms ease.
The problem was durability. For most women the benefit lasted up to about two years. Fat regrew. Symptoms recurred. Weight increased. Insurance usually denied coverage, so the whole thing had been a large out-of-pocket investment. And these procedures were often removing very large volumes of fat from women at very high weight — high risk on both counts.
The German surgeons were straightforward about the rationale. The purpose of operating, they said, was to slow the progression of the disease (the evidence for early treatment). Nobody argued that the disease would still progress — toward higher weight, greater disability, and loss of mobility, stability and function.
When I visited the LipoClinic in Mülheim in 2024, the protocol was still surgery: usually four consecutive procedures. That visit is a large part of why I practice differently now.
The distinction worth holding on to is this. In the areas actually treated, the improvement holds — Baumgartner followed sixty women for twelve years and found it did. What did not hold was the woman’s overall situation, because the disease carried on in areas never treated and the weight came back. That is a different problem from the operation failing, and it is the problem medical treatment now addresses. The durability evidence in full →
“Surgery relieved the symptoms and did nothing about the reason they came back. That isn’t an argument against operating. It’s an argument against operating alone.”
Dr. Jeffrey Ditesheim
How is lipedema treated
Every woman I treat is carrying two different things at once. One is a disease, and it comes out surgically. The other is ordinary weight and inflammation, and it comes down medically.
The surgical half
Water-assisted liposuction under a lymph-sparing protocol, removing the nodular fibrotic tissue that is generating the inflammation. No heat energy, which protects the veins and lymphatic structures that matter enormously here. Removing that tissue can re-establish normal lymph flow. How lymph-sparing technique works →
The medical half
Anti-inflammatory diet modification and, for many women, GLP-1 medication — reducing normal fat cells, controlling inflammation and holding weight stable so the surgical result lasts rather than fading at two years. GLP-1 medication and lipedema →
Why the medical half is not optional:
Weight gain, not age, is what I see driving progression in my patients, and GLP-1 medication does not touch lipedema tissue. See what combined treatment looks like →
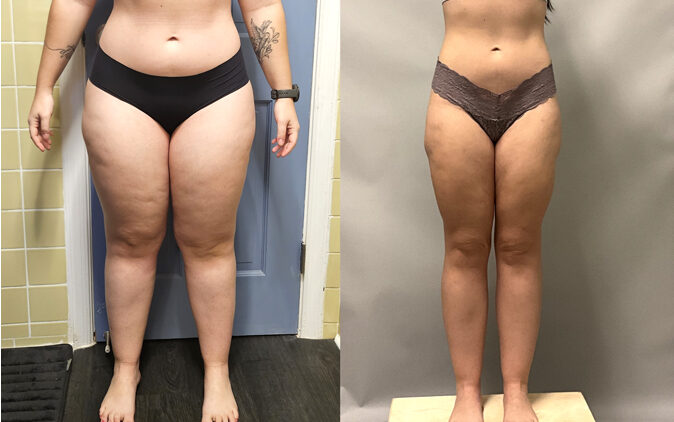
Lipedema surgery before & after results
Six patients, shown in two views each. These are all my own patients, photographed in my office. No stock images, no models, no retouching.


Lateral thighs, knees and legs
Her weight went from 185 to 147 on GLP-1 and her legs got smaller without changing shape. The weight was hers to lose. The shape was mine to correct. At sixteen months: no pain, full mobility, off the medication.
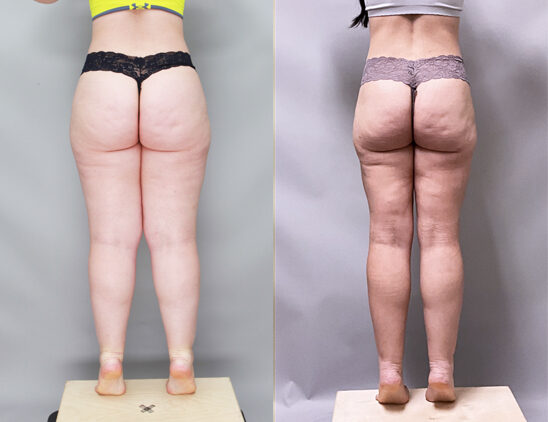
Buttocks, thighs, knees and legs
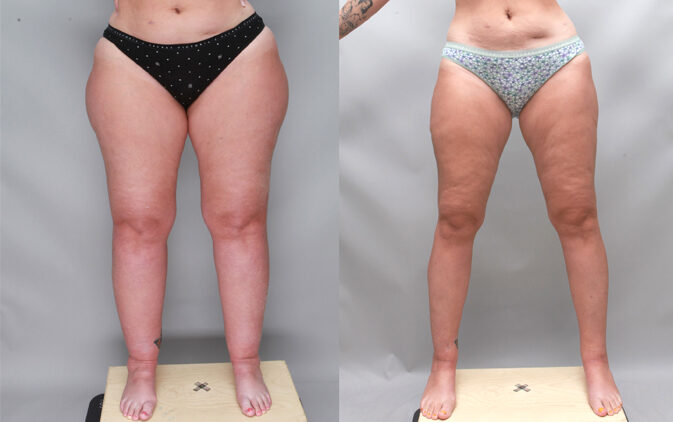
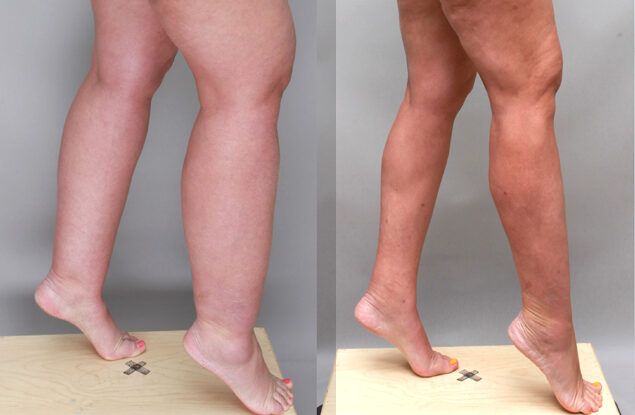
Buttocks, thighs, knees and legs


Arms, forearms, knees and legs


Thighs, knees and legs

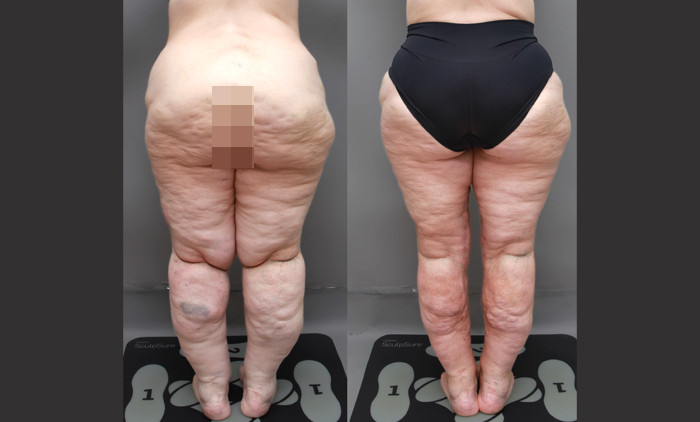
Thighs, knees and legs, with medial thigh lift
Surgery removes the disease tissue. The medication removes the ordinary weight around it and holds the result.
See three more cases of combined treatment →
Individual results vary. All photographs are of Dr. Ditesheim’s own patients, published with consent and shown without retouching.
Recovery, honestly
Compared with cosmetic liposuction, these are bigger operations. More fat comes out, and the area is almost always treated circumferentially — all the way around the limb, not just the part you can see in a mirror. Recovery reflects that, and you should plan for it rather than be surprised by it.
Preparation is part of the recovery
This is the part most women do not expect, and it is the part that makes the biggest difference. For most patients I plan on roughly three months of controlling inflammation before we operate — anti-inflammatory measures, diet, lymphatic therapy, flat-knit compression, and where appropriate GLP-1 medication. Within that, a minimum of three weeks of flat-knit compression and decompressive treatment immediately before surgery.
This is preparation, not an alternative to surgery. Fluid and ordinary body fat both disguise the disease, and both respond to treatment. Lipedema tissue does not. So once the swelling and the normal fat are controlled, what remains is the lipedema — and only then can I tell you honestly how many sessions you need.
A limb that arrives at surgery already decompressed heals faster, swells less afterward, and lets me remove diseased tissue more precisely. Preparation is not a formality. It is the single thing most within your control.
3+ weeks before
Flat-knit compression and decompressive treatment. GLP-1 where indicated.
First Week
Immediate recovery. Manage swelling, move early. Out-of-town patients stay in Charlotte for close follow-up.
Weeks 2–6
Recovery time for thighs and arms.
Months 2–4
Recovery time for legs.
Something I tell every patient beforehand: most of what you feel afterward is surgical healing discomfort, not lipedema pain. They are different sensations, and women who know that in advance handle the first weeks far better than women who do not.
What we are trying to achieve
What this means in practice
For a woman at lower weight with limited disease, it is possible to treat an entire extremity in a single session. With GLP-1 preparation it is sometimes possible to treat more than one area at once — legs and knees together, or thighs and arms. But where there is large-volume lipedema in a single area, that area alone will need more than one session, and no amount of preparation changes it.
My aim is one or two sessions rather than the three or four this disease historically required. I will not promise you a single operation. How much disease you have decides that, and I cannot honestly quote a session count until the swelling and the ordinary fat are down and I can see what is actually there. That is the practical argument for doing the preparation properly.
What I want you to understand before we operate
- This is not a cure. Surgery removes diseased fat and relieves symptoms. It does not cure the underlying disease, which is why the medical half matters.
- Advanced disease still takes longer. The more tissue involved and the longer it has been there, the more surgery and the more healing. Preparation shortens this; it does not erase it.
- Skin may not retract. Loose skin or contour irregularity can follow significant removal, and sometimes needs a separate excisional stage.
- Compression is not optional. Before surgery and after it, garments and follow-up are part of the result, not an accessory to it.
- The work continues afterward. Inflammation control and weight stability are what keep what we achieved.
What happens at a lipedema consultation?
This is the visit where both things happen — you find out what you have, and if it is lipedema, we make a plan to treat it. I meet with every person myself, and I would rather you knew in advance exactly what the hour involves.
Many women arrive here without a diagnosis at all. They are not coming to choose an operation; they are coming to find out why their legs hurt and why nothing they have been told to do has worked. Sometimes the most useful thing I do in that hour is give the thing a name.
The lipedema questionnaire, your medical information and photographs are requested ahead of the visit. I read them beforehand, so we are not spending your hour collecting information we could have had already. Educational material goes to you free in advance for the same reason — so the consultation can be about your case rather than about the disease in general.
A full review of your medical information and a physical examination. This is where lipedema is separated from lipohypertrophy, from lymphedema, from venous disease and from ordinary weight — conditions that look alike from across a room and are not alike at all. Baseline studio photographs are taken to document your anatomy before anything is done.
For most women, a plan for surgical treatment is made at this visit, starting with the preparation period described above. Medical treatment alone turning out to be enough does happen, but it is the exception, and usually only in early disease.
We help you obtain flat-knit compression garments with your insurance benefit, and refer you to a lipedema-trained lymphatic therapist in your own area for the work before and after surgery. Surgical planning and timing are settled here too.
A complete written consultation report is sent to you through our confidential portal — your diagnosis, your stage, and the plan, in writing, so you are not relying on what you remember from an emotional hour.
Spouses and partners are welcome and I encourage it. Two people hear more than one, and the person who will be helping you through recovery should hear it firsthand.
Expect an hour, often longer. This is not a fifteen-minute cosmetic surgery consultation, and it is not built like one.
“You may leave here being told you do not have lipedema. That is a real outcome and a valuable one, and I would rather give you that answer than operate on you.”
Dr. Jeffrey Ditesheim
The consultation fee, my surgical fees and what six of my own patients actually paid are all set out on a separate page, so that nobody has to ask. What treatment costs, told plainly →
What I've done in lipedema specifically
Board certification and thirty years of body contouring are the baseline. What matters more for this disease is whether the surgeon has gone looking for it.
National surgical guidelines panel
Selected as one of 12–15 physicians nationally — plastic surgeons, vein specialists and dermatologists who treat lipedema — to define and establish surgical guidelines for lipedema treatment.
Lipedema Society member
Active membership in the professional body dedicated to this disease.
Presented at FDRS
Presented the results of my own experience, and of my 2024 visit to Germany, at the Fat Disorders Resource Society meeting.
Went to the source
Visited the LipoClinic in Mülheim, Germany in 2024 to study the protocol at the center where much of the eighty-year body of work originates.
Questions women ask me
How do I know if I have lipedema or just obesity?
Lipedema fat is symmetrical, concentrated in the lower body and extremities, painful under pressure, bruises easily, spares the hands and feet, and does not respond to diet and exercise. Obesity is distributed across the whole body including the torso, and it isn’t tender. The two often coexist, which is part of why this gets missed. A proper examination separates them.
Can lipedema be cured?
No. It can be treated, and its progression can be controlled. Surgery removes the diseased tissue and the symptoms it generates; medical management addresses the inflammation and the weight. Together they can keep the disease from progressing to disability. That is a real outcome, and it is not the same as a cure.
Will the fat come back?
Not in the areas treated — a twelve-year follow-up found the improvement held. What does continue is the disease in areas left untreated, and ordinary fat if weight is regained. That is exactly the problem combined treatment is meant to solve. The durability evidence in full →
How many procedures will I need?
It depends on your stage and how much tissue is involved. Most of my patients need one or two sessions; I’ll tell you at consultation what I think your plan looks like. How many operations, and what limits it →
Is water-assisted liposuction better for lipedema?
For this disease, yes, and the reason is lymphatic preservation. It uses no heat energy, so it’s gentler on the veins and lymphatic structures — which matter enormously in a condition where lymph flow is already obstructed. Continuous fluid infusion also minimizes blood loss, which allows more tissue to be removed safely in one session.
Does insurance cover this?
We do not have contracts with any insurance company, so treatment here is out of network, but we support every patient fully in seeking her out-of-network benefits. I write a detailed consultation note addressing what insurers look for: the diagnosis, the functional impairment, the conservative treatment already tried, and the published evidence. I have also summarized the most recent studies in two documents you can download and send with your claim: the key studies and what the research says. Insurers have long argued that the evidence was not conclusive and that compression alone was enough. In September 2026 The Lancet published the LIPLEG randomized trial, which showed that conservative therapy is clearly inferior to surgery: 68% of women treated surgically had significantly less pain, compared with 7.6% who continued compression and lymphatic therapy. Several of my patients have obtained out-of-network reimbursement with good documentation and persistence. Insurance, cost and financing, in full →
What does treatment cost?
The first procedure is $15,000–$19,000, and that includes your surgical and nursing care before surgery, the surgery and recovery, and operating room and anesthesia care. Early disease usually needs just one; most women need one or two. What treatment costs, and what six of my patients actually paid →
Can I finance treatment?
Yes. We work with M-Lend, CareCredit and Cherry, and our patient coordinator can help you apply.
Can I be treated awake?
For selected patients, yes — water liposuction allows a single area to be treated under local anesthesia while you’re awake, with some limits on how much tissue can be removed that way.
I live far from Charlotte. Can we start remotely?
Yes. The first consultation can be virtual; send your questionnaire, records and photographs ahead. One visit before surgery must be in person, usually within a month of your surgery date (closer to surgery if you’re coming from overseas). I recommend staying in Charlotte for a week after surgery for close follow-up and supportive therapy. Back home, we coordinate a lymphatic therapist near you, follow you through the first three months, and encourage a yearly visit after that.
Can men develop lipedema?
Yes, though it’s far less common. The strong link to hormonal change is why this disease predominantly affects women.
More on lipedema cost, GLP-1, and research
Each of these is written the same way as this one — by me, about my own practice and the evidence I rely on.
What treatment costs, told plainly
The fee for a first procedure and what it includes, what six of my patients actually paid, costs around the US and in Germany, insurance and financing.
GLP-1 medication and lipedema
What it can and can't do to lipedema tissue.
What the research says
Ten questions women actually ask me, answered from the published evidence and rated for how solid that evidence is. Where it is weak, I say so.
The key studies, and what each one proves
Eight studies listed by what each establishes, with full references. Written for a physician unfamiliar with lipedema, or for documenting why surgical treatment is medically justified. Printable.
Bring the questionnaire. Let's find out what you actually have.
A consultation gives you a diagnosis, a stage, and a plan — or a clear answer that this is something else. Both of those are worth having, and you have waited long enough for either one.
Mon–Thu 8am–4pm · Fri 8am–12pm · 9336 Blakeney Center Drive, Suite 130, Charlotte NC
Written by Jeffrey A. Ditesheim, MD, FACS · About Dr. Ditesheim · Ditesheim Cosmetic Surgery, 9336 Blakeney Center Drive, Suite 130, Charlotte, NC 28277 · 704-542-8686. This page is educational and is not a substitute for individual medical advice.